Uncovering the Prescribing Cascade
In the complex world of modern medicine, the pursuit of better health can sometimes lead to unintended consequences. A major study recently published in the BMJ has highlighted a troubling phenomenon known as the 'potentially inappropriate prescribing cascade' (PIPC). This occurs when a side effect triggered by an initial medication is misconstrued as a new, unrelated medical condition, prompting a doctor to prescribe a second medication to treat that 'new' symptom. Rather than curing the patient, this chain reaction often compounds health risks and increases financial burdens on the healthcare system.
Led by Dr. Paula Rochon of the Lunenfeld-Tanenbaum Research Institute, an international team of experts spent years analyzing population-level data to map these sequences. By comparing extensive clinical data with a curated list of potential drug interactions, the researchers identified 24 distinct, common, and harmful prescribing cascades that occur frequently in clinical practice. This research marks a significant step forward in understanding the hidden dangers of polypharmacy, particularly in aging populations who are often prescribed multiple drugs simultaneously.
The Mechanism of Misdiagnosis
The study illustrates how easily these cycles begin. A classic example cited by researchers involves non-steroidal anti-inflammatory drugs (NSAIDs), which are widely prescribed for pain management. These medications are known to elevate blood pressure in many patients. If a physician views the resulting hypertension as an independent diagnosis rather than a side effect of the pain medication, they may prescribe an anti-hypertensive drug. This creates a cascade where a secondary medication is introduced to solve a problem that arguably shouldn't exist in the first place.
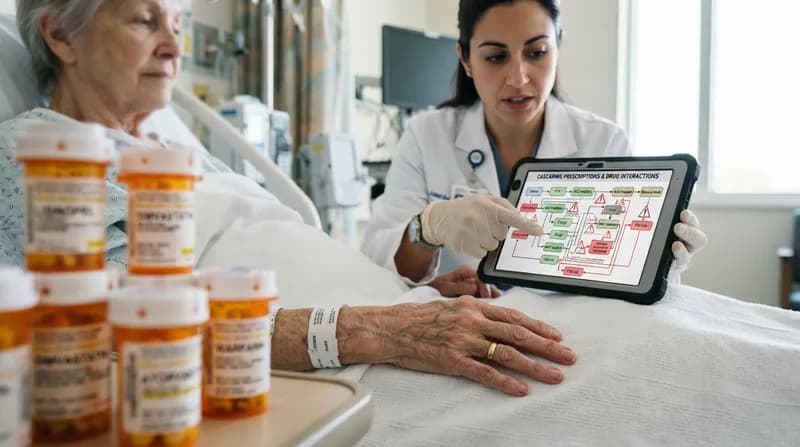
Older adults and mature women, in particular, face a disproportionately high risk. Due to a higher prevalence of chronic conditions, these demographic groups are more likely to be on complex medication regimens. As the number of daily pills increases, the likelihood of a symptom being linked back to the original drug decreases, making it increasingly difficult for both clinicians and patients to untangle the web of prescriptions. The researchers emphasize that the problem isn't just about the medications themselves, but the lack of communication regarding when each drug was introduced and the original intent behind the prescription.
Why it Matters
The identification of these 24 cascades serves as a wake-up call for the medical community to shift toward more holistic, patient-centered medication reviews. Without a systematic way to track the timeline of drug introductions and their corresponding symptoms, patients risk enduring 'treatment' for conditions caused entirely by their own pharmacopeia.
- Improved Patient Safety: Identifying these patterns early prevents unnecessary exposure to multiple pharmaceutical agents and their combined side effects.
- Healthcare Cost Reduction: Eliminating redundant prescriptions reduces avoidable spending for both individual patients and provincial or national health systems.
- Better Clinical Communication: The findings underscore the urgent need for structured conversations between providers and patients regarding the necessity of continuing older prescriptions.
The Role of Tech and Pharmacists
To combat this, the research team advocates for the integration of intelligent digital tools. Automated clinical decision support systems could be engineered to flag potential prescribing cascades in real-time. By monitoring electronic health records, these systems could alert a physician if a new drug order coincides with a known side effect of an existing one, providing a crucial 'stop-and-think' moment before a new prescription is finalized.
Furthermore, the study suggests that the solution is not entirely digital. Pharmacists possess a unique vantage point in the healthcare ecosystem and are well-positioned to serve as a secondary line of defense. By participating more directly in the collaborative care team, pharmacists can conduct thorough medication audits, identifying potential cascades that might be missed during brief physician consultations. Ultimately, the goal is to replace the current reactive, additive model of prescribing with a more thoughtful, evidence-based approach that prioritizes the patient's long-term well-being over the immediate management of individual symptoms.